Harper Washington · 30 September 2026
Visual Mapping Integration in Tracking Patient Care Coordination Across Multi-Site Hospital Networks
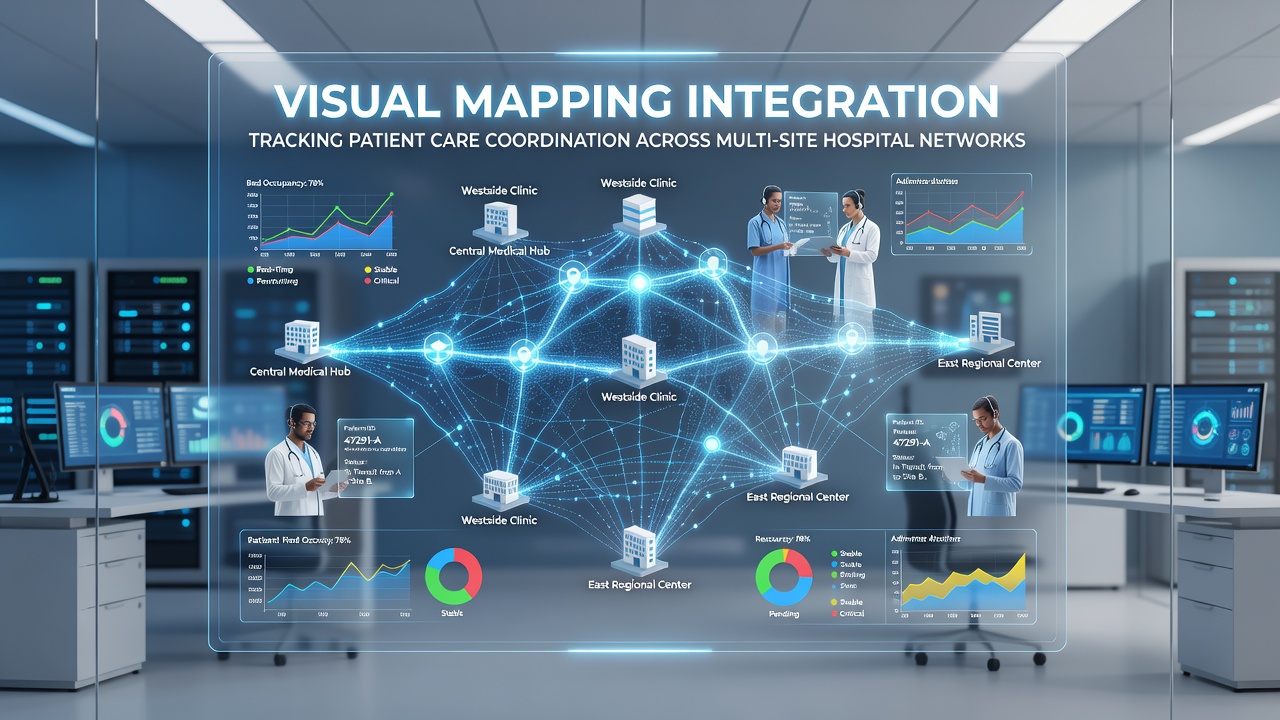
Healthcare networks operating across several locations rely on integrated visual mapping systems to monitor patient movements and treatment sequences in real time, and these platforms combine electronic health records with geographic and workflow overlays so staff can trace cases from admission through discharge without switching between separate databases. Data flows from individual sites feed into a central interface that highlights delays or resource gaps while maintaining compliance with privacy regulations in multiple jurisdictions.
Core Components of Visual Mapping Systems
Systems of this type pull structured data from electronic health records, scheduling software, and diagnostic equipment then render it as interactive diagrams that update continuously as new entries appear, and researchers at several academic medical centers have documented how color-coded nodes represent different stages of care such as initial assessment, specialist consultation, and transfer between facilities. The integration layer uses standardized APIs that align with HL7 and FHIR protocols, allowing hospitals in the United States, Canada, and the European Union to exchange information without custom coding for each partnership.
Staff at participating sites receive role-based views that filter information according to clinical need, and one multi-state network reported that adoption of these shared visualizations reduced duplicate test orders by aligning records across emergency departments and outpatient clinics. Training programs emphasize interpretation of the maps rather than data entry, which shortens onboarding time for new clinicians joining the network.
Implementation Patterns Observed in 2026
In September 2026 several large hospital groups completed phased rollouts that synchronized visual mapping tools with updated federal interoperability requirements, and records from those deployments show measurable decreases in average length of stay for patients transferred between campuses. The projects typically begin with a pilot at two sites before expanding, during which teams map existing workflows to identify which data points require the most frequent updates. Integration teams then configure alerts that flag when a patient’s care plan deviates from expected timelines, prompting coordinators to intervene before minor issues compound.
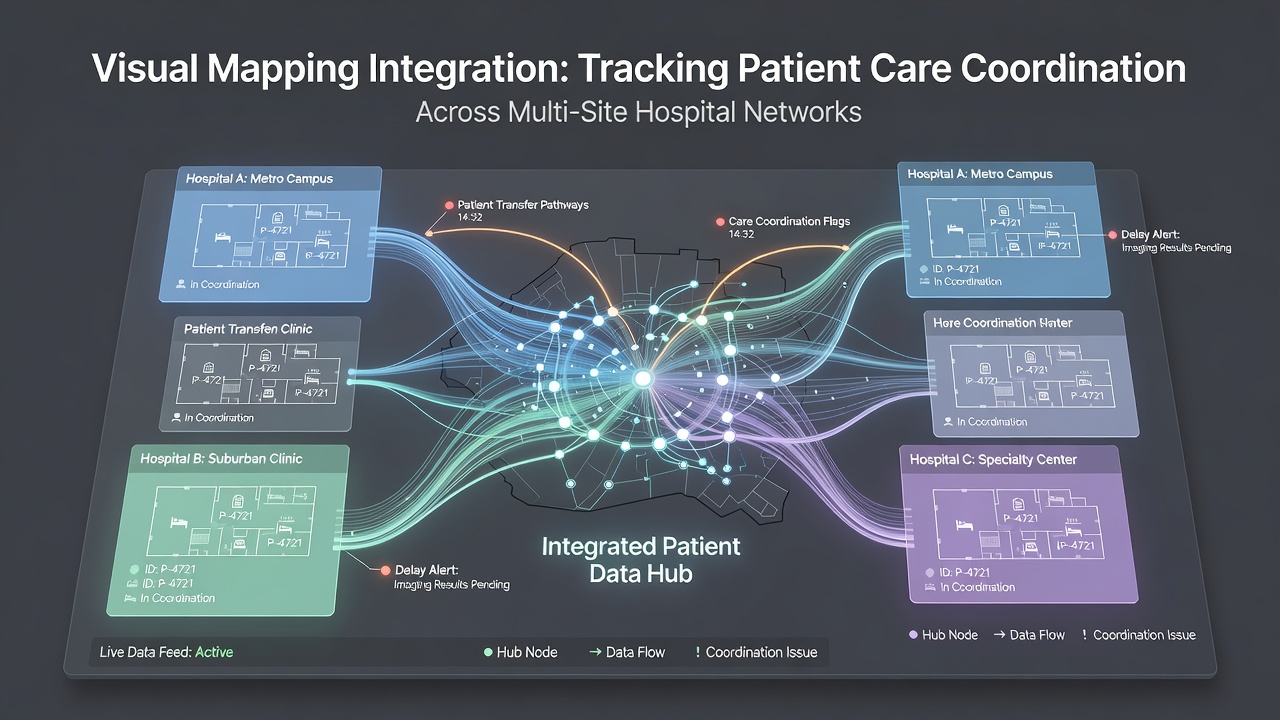
Observers note that success depends on consistent data governance rather than the software itself, because mismatched terminology between sites can produce misleading visual clusters even when underlying records remain accurate. Hospitals that established shared data dictionaries before launch experienced smoother transitions and fewer post-implementation adjustments.
Coordination Across Geographic and Organizational Boundaries
Multi-site networks often span different regulatory environments, and visual mapping platforms accommodate these variations by displaying jurisdiction-specific compliance flags alongside clinical timelines. A Canadian provincial health authority and several U.S. academic centers have shared anonymized case studies demonstrating how such flags prevented scheduling conflicts during cross-border specialist consultations. The maps also surface supply chain dependencies, revealing when equipment or medication shortages at one location affect downstream facilities in the same network.
According to information published by the Agency for Healthcare Research and Quality, coordinated visualization tools correlate with improved handoff accuracy when patients move between inpatient and ambulatory settings. Separate analyses from European research consortia indicate similar patterns when regional hospitals adopt common mapping standards. These findings rest on aggregated operational metrics rather than controlled trials, yet they provide consistent directional evidence across different health systems.
Technical Considerations and Data Security
Security protocols embed encryption at the visualization layer so that maps transmitted between sites remain protected even when viewed on mobile devices used by traveling specialists, and audit logs record every query against the central repository. Network administrators configure role-based access that limits which staff can expand or collapse specific branches of a patient pathway, thereby reducing exposure of sensitive details. Backup visualization instances run in geographically dispersed data centers to maintain continuity during regional outages.
Updates to the underlying mapping engine occur through staged releases that allow individual sites to test compatibility before full deployment, and this approach minimizes disruption to ongoing care coordination activities. Technical documentation from vendors shows that most integrations complete within existing firewall rules once initial authentication certificates are exchanged.
Conclusion
Visual mapping integration supplies a consolidated view of patient care sequences across dispersed hospital locations while drawing on existing electronic records and scheduling systems, and ongoing deployments through 2026 continue to refine how networks surface coordination gaps in actionable formats. Continued alignment with interoperability standards and data governance practices determines whether these tools deliver sustained operational improvements across varied regulatory landscapes.